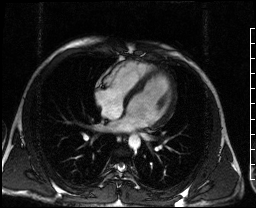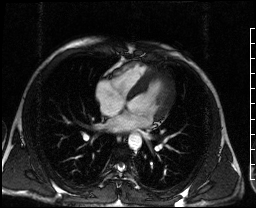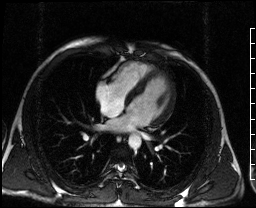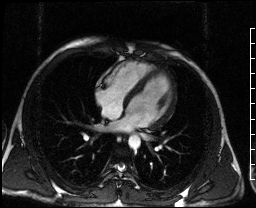
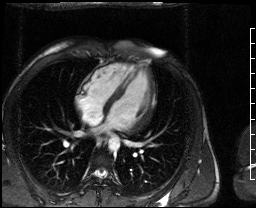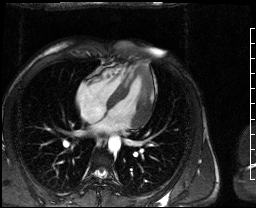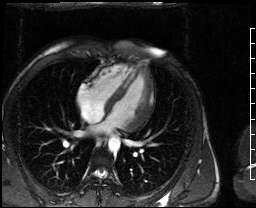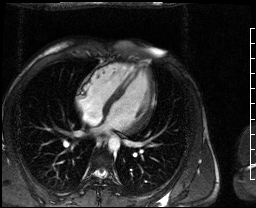
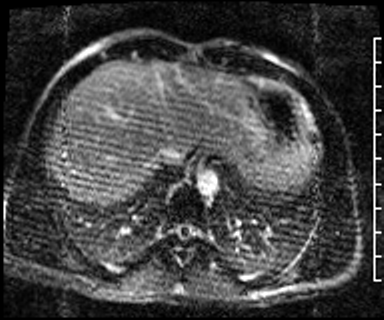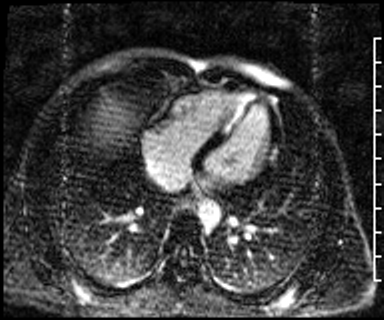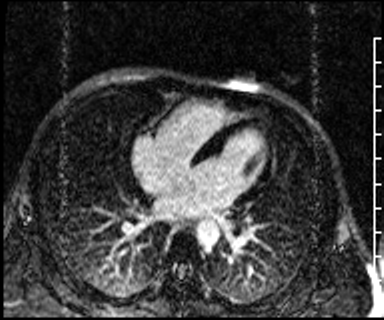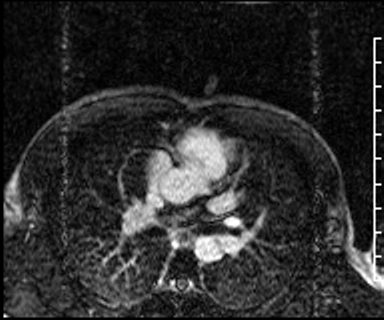
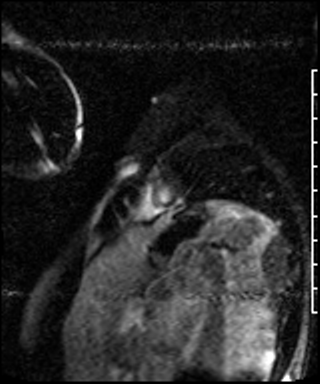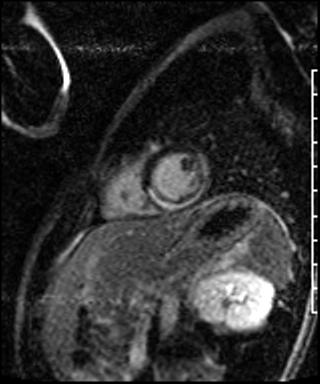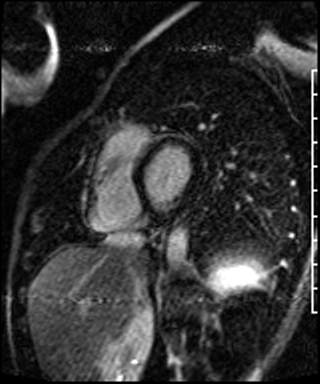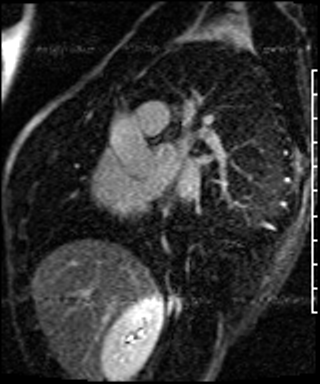
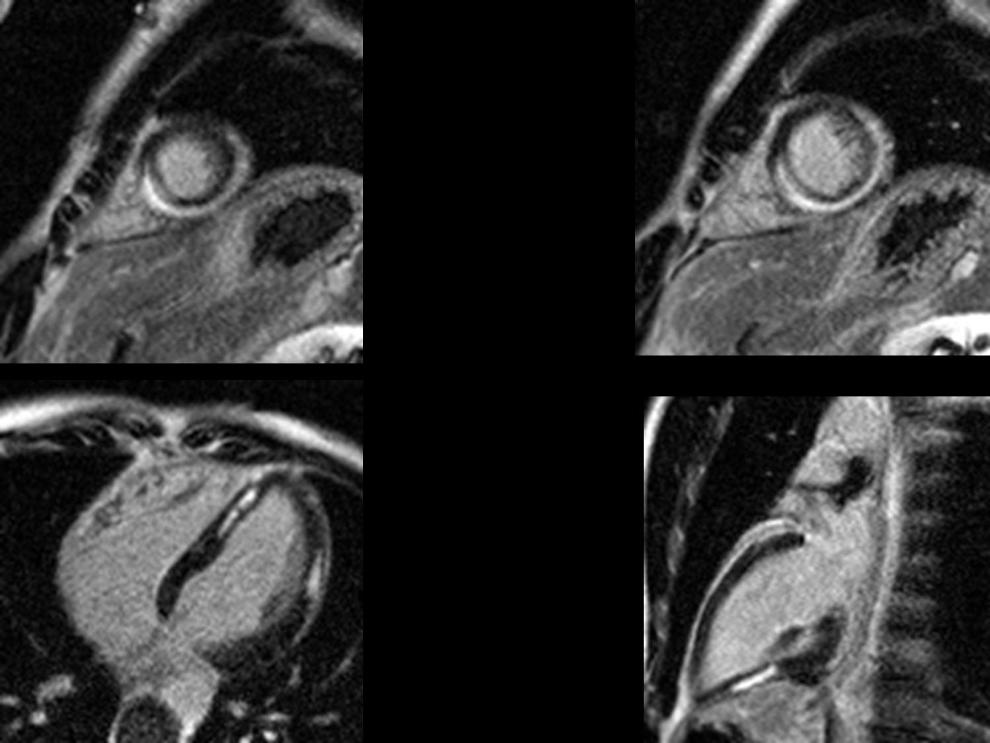
Radiologic Findings Selected Cardiac MRI Images. Pre-contrast 4-chamber SSFP cine (Fig.1) shows the left ventricular cavity is normal in size and function. There is no regional or global wall motion abnormality. The ejection fraction is estimated at least 55%. The right ventricle is also normal in morphology and function. No mitral or tricuspid regurgitation is appreciated. Post-contrast enhanced 4-chamber SSFP cine (Fig. 2), post-contrast axial VIBE (fat-suppressed) (Fig. 3), and post-contrast short-axis SSFP cine (Fig. 4) images demonstrate mid- myocardial and epicardial enhancement involving the inferior, inferoseptal, inferolateral and lateral walls at the mid ventricular and apical levels in a non-coronary distribution. These findings are confirmed on the 10 minute delayed post-contrast myocardial signal-nulled-T1 weighted short axis (Fig. 5A and 5B) short-axis, 4-chamber (Fig. 6) and 2-chamber (Fig. 7) delayed images. Note the absence of sub-endocardial enhancement (Images courtesy of Jen Hubert, MD, VCU Medical Center). Diagnosis: Viral Myocarditis
Also see Cardiothoracic Pulmonary Imaging Correlation Conference Case of the Week from June 4-11, 2010
Differential Diagnosis
Myocarditis of other etiologies
Discussion
The myocardium is subdivided into subendocardial, subepicardial, and mesocardial regions. The subendocardium is the innermost region, lying in closest proximity to the ventricular blood pool, and is the region most sensitive to ischemia and infarction. The subepicardium is the outermost region, located farthest away from the blood pool and in close proximity to the pericardium. Subepicardial enhancement is seen in the majority of cases of myocarditis; however focal areas of transmural enhancement may be seen in severe cases. The mesocardium or mid-myocardial region lies between the subendocardium and subepicardium. Myocarditis and various infiltrative cardiomyopathies can cause delayed enhancement in the mid-interventricular septum. However, the abnormalities will not be limited to the mid-interventricular septum, but will be more pronounced in other myocardial regions as well. The distribution and pattern of delayed enhancement allows radiologist to differentiate ischemic from non-ischemic disease (Table -1) and thus appropriately guide patient management. Patterns of abnormal delayed contrast enhancement include diffuse, patchy, and nodular.
Table-1: Differential Diagnosis based on Pattern of Delayed Contrast Enhancement Subendocardial Vascular Subendocardial Non-vascular Subepicardial Mesocardial Transmural Ischemia Amyloidosis Myocarditis Hypertrophic Cardiomyopathy Infarction Infarction Loeffler Endocarditis Sarcoidosis Dilated Cardiomyopathy Myocarditis (severe) Histiocytoid Cardiomyopathy Anderson-Fabry Pulmonary Artery Hypertension Sarcoidosis (chronic) Systemic Sclerosis Myocarditis Post Cardiac Transplantation
Clinical Findings
Myocarditis is a common cause of non-ischemic cardiomyopathy. The clinical presentation is often non-specific, ranging from vague to severe chest pain; to frank heart failure and sudden death. Markers of myocardial damage, troponin or creatine kinase are elevated. Viral infection (parvovirus B-19; adenovirus) is the most common cause of myocarditis. Other possible causes include various drug toxicities and autoimmune disorders such as systemic lupus erythematosus (SLE) and mixed connective tissue diseases (MCTD). Because the clinical presentation is often nonspecific, diagnosis is dependent on clinical suspicion, laboratory data, and endomyocardial biopsy in select cases. When cardiac MR imaging findings are concordant with the clinical suspicion, biopsy may potentially be avoided.
Prognosis
- Most patients: fully recover with supportive measures
- One-third of patients: develop dilated cardiomyopathy
- An acute myocardial infarction-like syndrome with normal coronary arteries: good prognosis
- Heart failure, even with dilated left ventricle: may still have a good prognosis
- Ventricular dysrhythmias and high-degree heart block: poor prognosis
- Loss of right ventricular function: strong predictor of death
CAVEATS
- Ischemic, or infarct-related, cardiomyopathy: tends to cause delayed enhancement in the subendocardium or transmurally and follows a specific vascular territory
- Non-ischemic cardiomyopathies: tend to cause delayed enhancement in more than one vascular territory when restricted to the subendocardium or to spare the subendocardium
- Delayed subepicardial contrast enhancement: highly suggestive of myocarditis
- Myocarditis causes up to 20% of all cases of sudden death
- Delayed contrast enhancement limited to mesocardium in the mid-interventricular septum: most often associated with hypertrophic cardiomyopathy (HCM) and dilated cardiomyopathy
Selected Readings
- Cummings KW, Bhalla S, Javidan-Nejad C, et al. A Pattern-based Approach to Assessment of Delayed Enhancement in Non-ischemic Cardiomyopathy at MR Imaging. RadioGraphics 2009; 29: 89-103.
- Grizzard JD, Judd RM, Kim RJ. Non-Ischemic Cardiomyopathies. In: Cardiovascular MRI in Practice. Springer-Verlag, London; 2008: 3237.
- Grizzard JD, Judd RM, Kim RJ. Teaching File Case 138. In: Cardiovascular MRI in Practice. Springer-Verlag, London; 2008: 249-250.
Original case written by its authors at Virginia Commonwealth University and published at this address as part of a weekly teaching collection. Reproduced here as an archive.