Differential Diagnosis
- Respiratory bronchiolitis (RB) (cigarette smokers)
- Respiratory bronchiolitis-interstitial lung disease (RB-ILD) (cigarette smokers)
- Desquamative interstitial pneumonia (DIP) (cigarette smokers)
- Pneumocystis jiroveci pneumonia (immunocompromised patients)
Discussion
Background
Hypersensitivity pneumonitis (HP), also known as extrinsic allergic alveolitis (EAA), is an immunologic reaction to inhaled organic antigens (e.g., animal proteins, bacteria, fungi, and various chemicals) that produces a diffuse interstitial granulomatous lung disease that varies in its intensity, clinical presentation, and natural history.
Etiology
There are a variety of known antigens as indicated above. Most exposures are occupational or recreational in nature. Farmer’s lung and bird fancier’s lung are the most common forms of HP. Farmer’s lung results from exposure to a bacterium in moldy hay. Bird fancier’s lung is a result of chronic exposure to proteins from bird feathers, serum, and or excrement. This particular patient had 6 exotic birds at home that were imported from overseas. Her symptoms gradually developed over the first two months after having brought the birds into her home.
Clinical Findings
HP has been classified into acute, subacute, and chronic forms although patients tend to present clinically with subacute or chronic disease. Patients with acute HP present with a sudden onset of flu-like symptoms (e.g., fevers, chills, malaise, cough, and shortness of breath) within a few hours of heavy exposure to the antigen. Subacute HP is somewhat more insidious. Affected patients become symptomatic with cough and dyspnea over a period of days or weeks following intermittent and continuous exposure to low dose antigens. Chronic HP presents following very-low level antigenic exposures for a prolonged period of time with progressive dyspnea.
Pathology
Acute
- Intraalveolar inflammatory exudates and edema
- Neutrophilic infiltration of the respiratory bronchioles and alveoli
Subacute
- Chronic bronchiolitis with peribronchial interstitial inflammation
- Non-caseating granulomas
- Scattered centrilobular inflammatory nodules with lymphocyte predominance
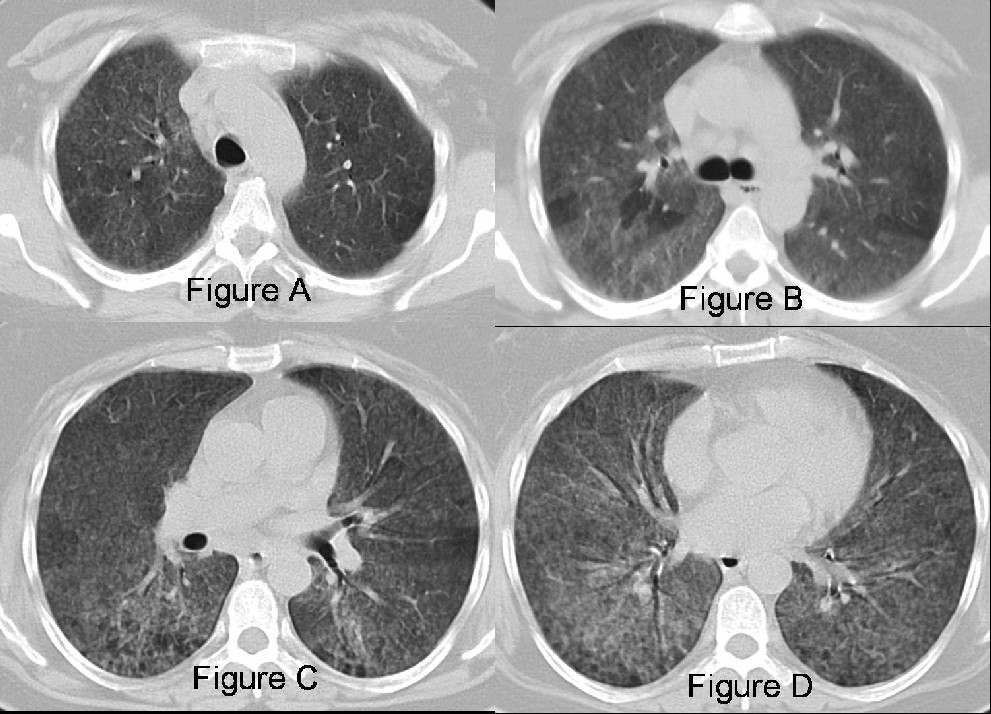
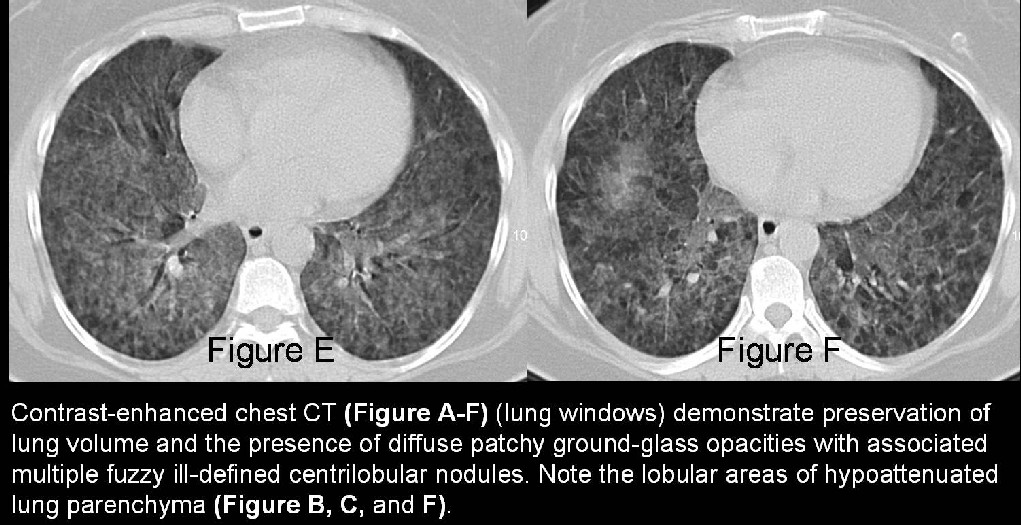
- Lobular areas of spared or hypoattenuated lung
Chronic
Interstitial fibrosis
Imaging
Radiography
Acute
- Often normal
- Fine military pattern
- Diffuse pulmonary opacities that mimic pulmonary edema
- Mid-to-lower lobe predominance
Subacute
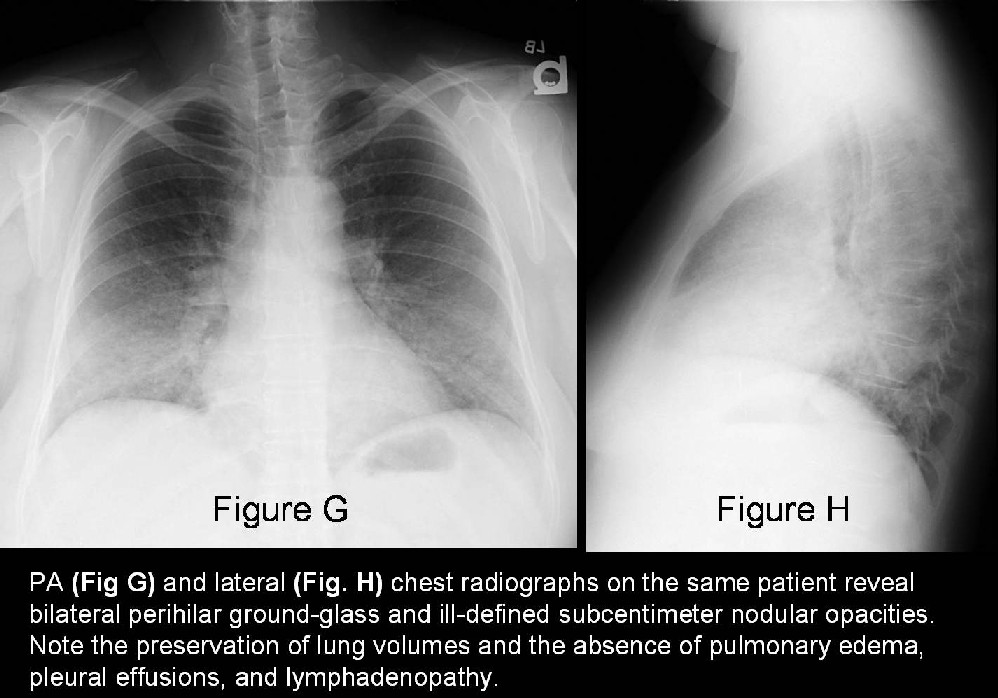
- Most often abnormal (Fig. G and Fig. H)
- Diffuse ground glass opacities (Fig. G and Fig. H)
- Poorly defined subcentimeter or miliary nodules (Fig. G and Fig. H)
- Diffuse or middle and lower lobe predominance (Fig. G and Fig. H)
- Preservation of lung volume (Fig. G and Fig. H)
Chronic
- Fibrotic changes (reduced lung volumes)
- Coarse, irregular, linear opacities
- Usually no lymphadenopathy or pleural disease
- Mid-to-lower lung predominance
- Honeycombing with advanced cases (mimic IPF)
CT/HRCT
Acute and Subacute
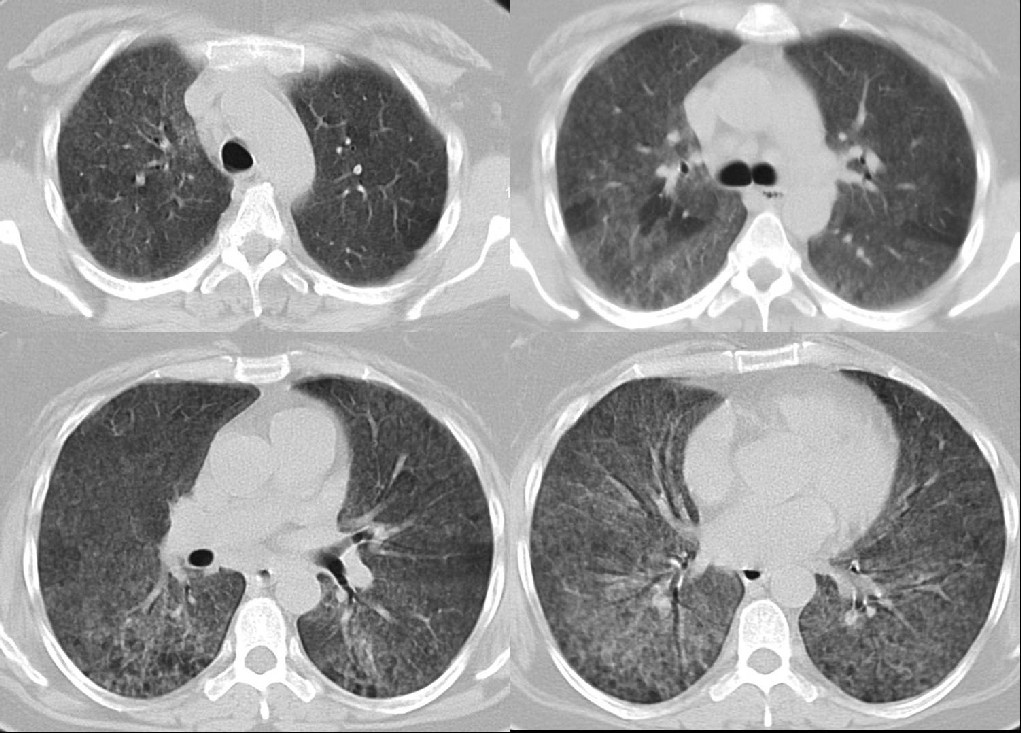
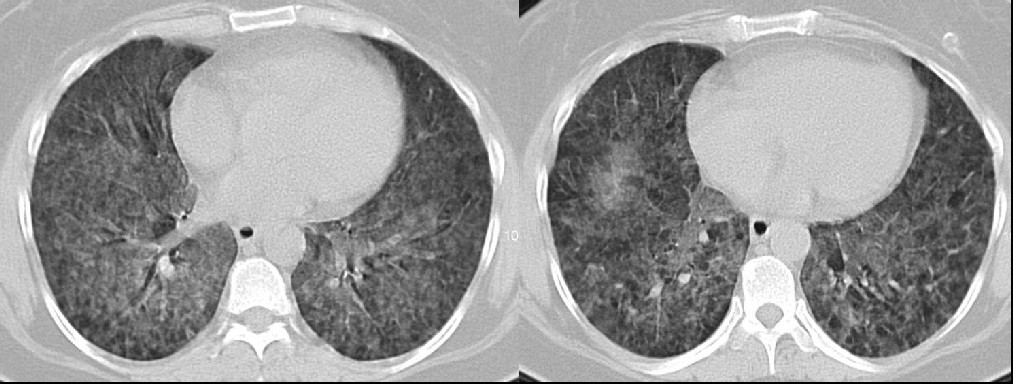
- Patchy or diffuse bilateral ground-glass opacities with associated poorly defined subcentimeter or miliary nodular opacities (Figure A-F)
- Fuzzy or ill-defined centrilobular nodules (Figure A-F)
- +/- Air trapping on expiratory imaging
- Preserved lung volume (Figure A-F)
Chronic
- Fibrosis (mid-to-lower lung predominance)
- Architectural distortion and volume loss
- Reticular opacities; patchy, central, occasionally peripheral
- Areas of mosaic perfusion
- Usually no lymphadenopathy or pleural disease
Treatment
- Cessation of exposure to and/or removal from the responsible antigen
Prognosis
- Following cessation of exposure to the antigen: symptoms and imaging abnormalities should resolve (acute and subacute cases)
- Continued exposure: progression to fibrosis and irreversible lung damage
Caveats:
- The two most common forms of HP are farmer’s lung and bird fancier’s lung.
- HP may also result from exposure to organisms growing in stagnant water (e.g. swimming pools; hot tubs; central heating systems).
- A high index of suspicion and inquisition about a given patient’s potential environmental, occupation, and recreational exposures is critical in making the diagnosis.
Suggested Reading
- Parker MS, Rosado-de-Christenson ML, Abbot GF. Diffuse Lung Disease. In: Teaching Atlas of Chest Imaging. Thieme Medical Publishers, Inc. 2006. P. 490-492.
- Sahin H, et al. Chronic Hypersensitivity Pneumonitis: CT Features – Comparison with Pathologic Evidence of Fibrosis and Survival. Radiology 2007. 244: 591-598.
- Silva CI, et al. Hypersensitivity Pneumonitis: Spectrum of High-Resolution CT and Pathologic Findings. AJR 2007. 188 (2): 224-244.
- Silva CI, et al. Chronic Hypersensitivity Pneumonitis: Differentiation from Idiopathic Pulmonary Fibrosis and Nonspecific Interstitial Pneumonia by Using Thin-Section CT. Radiology 2008; 246: 288-297.
Original case written by its authors at Virginia Commonwealth University and published at this address as part of a weekly teaching collection. Reproduced here as an archive.